Medical Devices and Technology
What Your Scan Already Knows: Medical Imaging Technology’s Quiet Shift Toward Opportunistic Screening
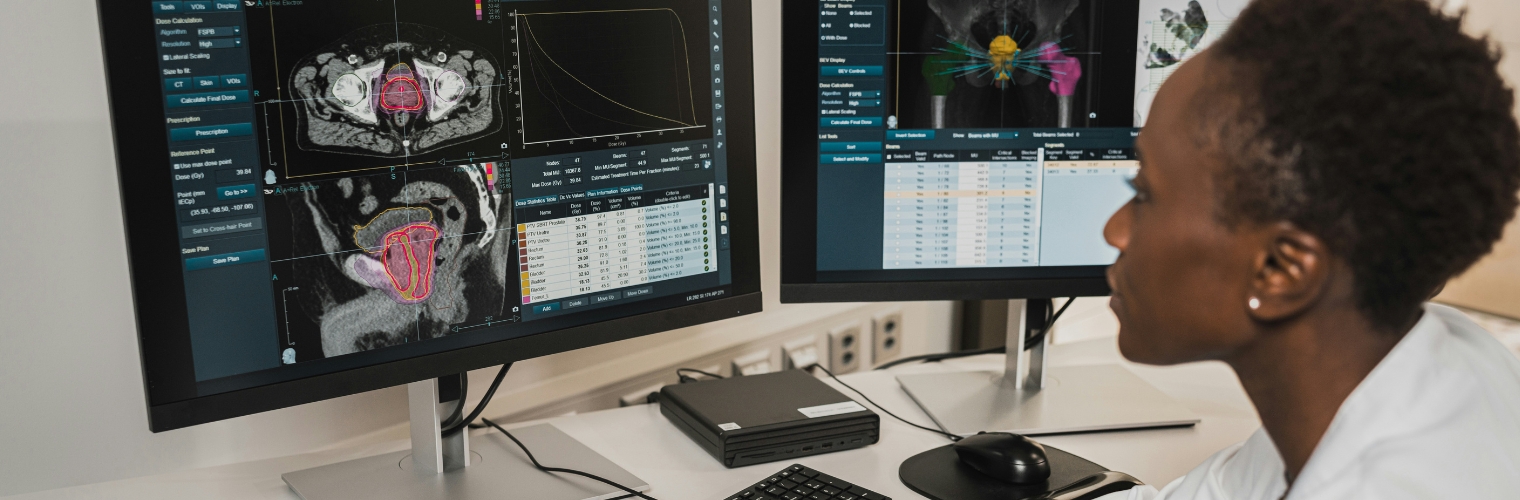
Image Courtesy: Unsplash


A scan ordered for one problem carries information about dozens of others, sitting quietly inside the pixel data long after the radiologist signs the report. This blog looks at how modern medical imaging technology is starting to surface that hidden signal, what opportunistic screening actually finds inside routine scans, where the responsibility for catching it lands, and what a second read of the same file could mean for patients who assumed the story ended at diagnosis.
Also read: Inside Photon-Counting CT: A New Standard for Medical Imaging Technology
Is a Scan Ever Really About One Thing?
A chest CT ordered to rule out pneumonia captures the lungs, sure, but the same pass through the body also captures bone density along the spine, the amount of visceral fat around the organs, and calcium buildup in the coronary arteries. None of that shows up in a routine radiology report written for the original question. Radiologists are calling this opportunistic screening, a term for extracting cardiometabolic and skeletal risk signals from scans that were ordered for something else entirely. The image already contains the answer. Somebody just needs a reason to look.
Medical Imaging Technology Is Learning to Read Past the Original Order
Medical imaging technology built around single-task algorithms reads a scan the way the original order intended, checking one specific question and stopping there. Newer foundation models trained across broader imaging datasets work differently, pulling multiple signals from the same file in a single pass. Google’s MedGemma and MedSigLIP models, released as open tools in early this year, point toward this direction: systems trained to interpret imaging findings alongside other clinical context, rather than isolating one narrow task per algorithm. The shift matters because most opportunistic findings need exactly this kind of broader read to surface at all.
Which Signals Are Sitting There Unused?
Three categories keep surfacing across current opportunistic screening research:
- Coronary calcium shows up on nearly any chest CT
- Bone density comes through on routine abdominal scans
- Visceral fat gets measured without a dedicated scan
None of these require an additional appointment, an extra dose of radiation, or a new order from a referring physician. The data sits inside a scan that already happened.
Radiologists Were Never Asked to Catch Everything
A radiologist reading a scan works against the clinical question on the order form, and incidental findings outside that scope have historically depended on individual habit rather than a defined workflow. That inconsistency becomes a real problem once the technology can reliably surface findings human reader never specifically looks for. The question shifts from what a radiologist happened to notice toward what a system was capable of finding and whether that finding reached anyone at all.
FAQ: Should a Second Opinion Come From Data You Already Have?
Patients rarely ask for a second read of a scan they already paid for and already have on file. Once opportunistic screening tools mature past pilot programs, that assumption gets harder to defend. A single archived scan could carry years of preventive value sitting unread, waiting on a workflow that decides whose job it is to look again. The most interesting question in imaging right now sits inside every scan already taken, ahead of whatever comes out of the next scanner release.